Patient education
Lumbar disc replacement
Lumbar disc replacement removes a damaged disc in the low back and places an artificial disc. The aim is to ease disc-related back pain while keeping motion at that level when the anatomy fits.

- Removes the problem disc through the front of the abdomen
- Places an artificial disc
- Keeps motion at that level when it fits
What it is
The discs in the low back sit between the lumbar vertebrae. When a disc wears, loses height, or becomes painful, it can cause low back pain that limits daily activity. Sometimes that pain is severe and lasts for months. Leg symptoms may be present as well.
In lumbar disc replacement, also called lumbar disc arthroplasty or artificial disc replacement, the surgeon removes the problem disc through a small incision in the front of the abdomen and places an artificial disc. Materials and designs vary by implant. Many use metal endplates with a plastic core designed to allow controlled motion.
Anterior lumbar fusion also removes the problem disc, then stabilizes the level so those bones can grow together. Disc replacement aims to keep more motion at the treated level than fusion does. Which path fits depends on your symptoms, imaging, bone quality, facet joints, and overall spine alignment.
Motion preservation may lower stress on nearby levels compared with fusion in some studies, but it does not guarantee that adjacent levels will stay problem-free. That question is still studied in the spine literature.
What the implant can look like
These images show one artificial disc family used for patient education. Other implant designs also exist.
-
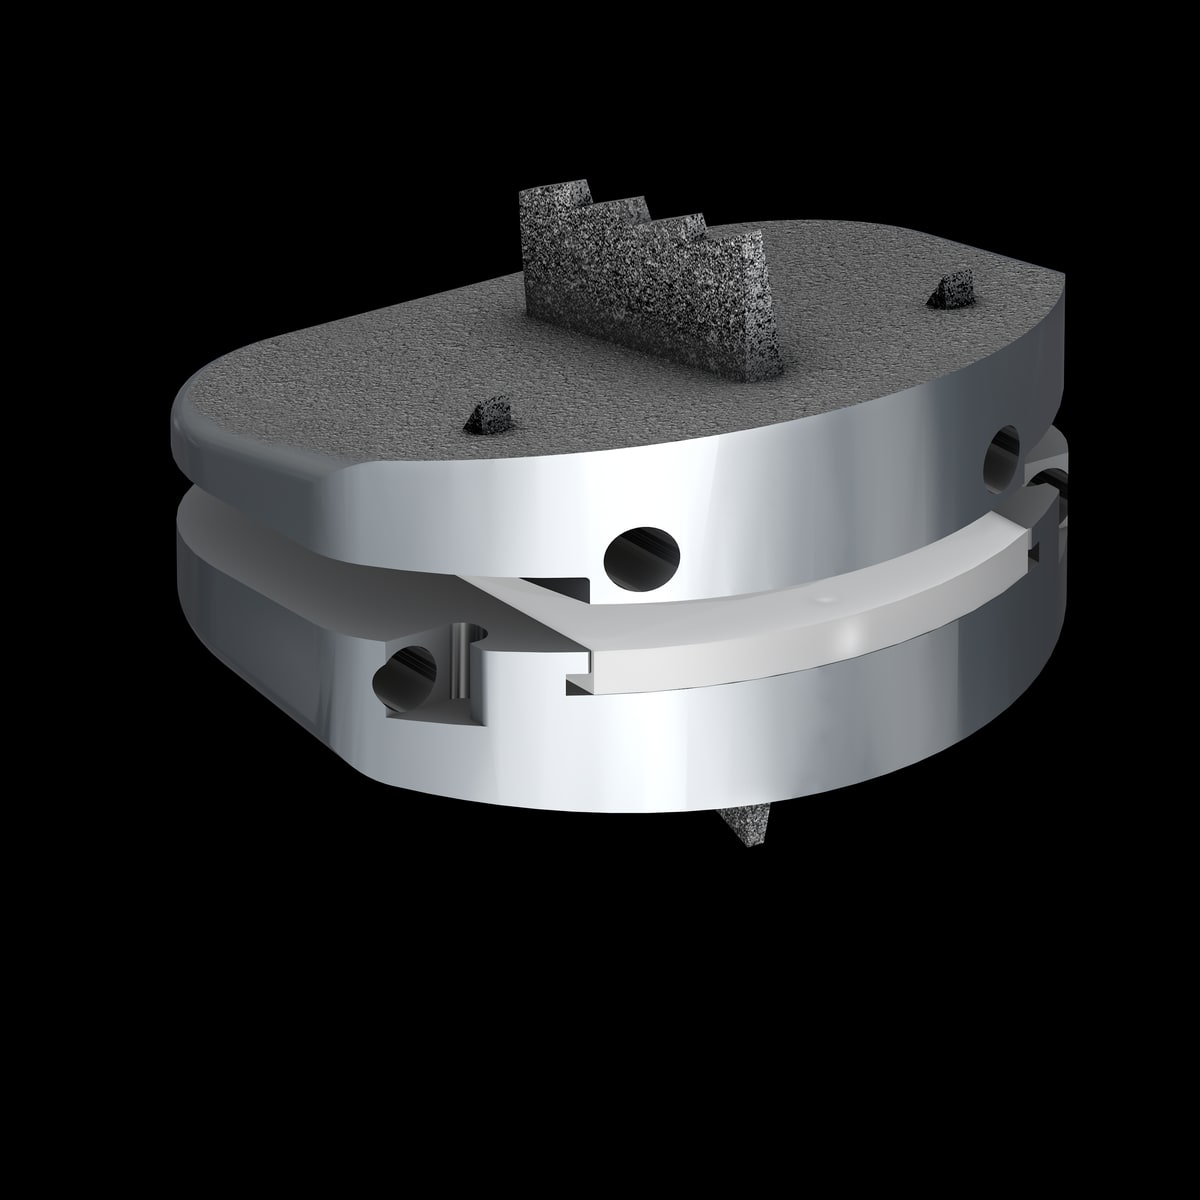
Example lumbar artificial disc (prodisc L). Metal endplates sit against the bone; a plastic core allows controlled motion. -
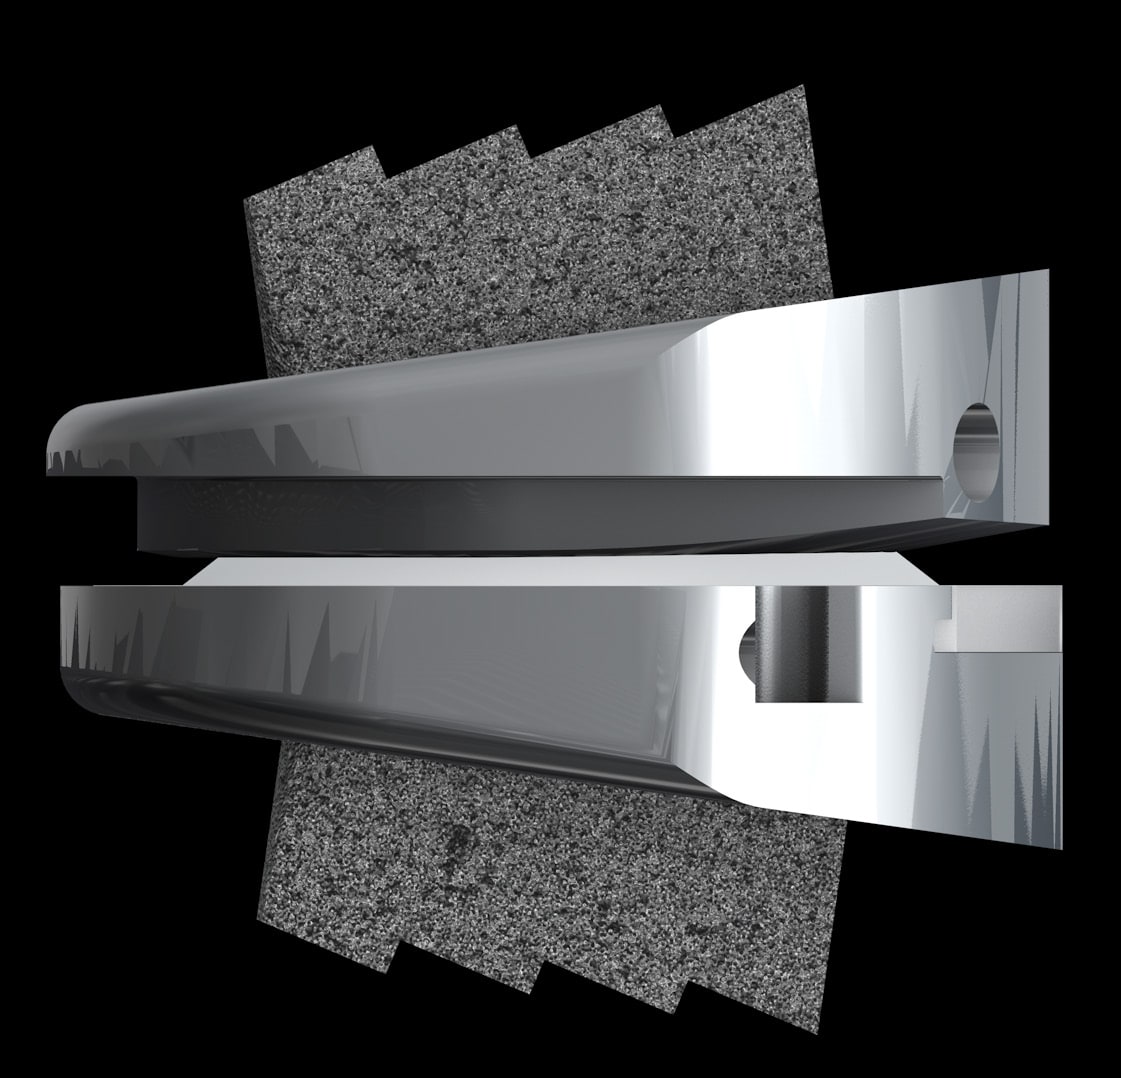
Close view of how the metal endplates sit against the bone after the damaged disc is removed. -
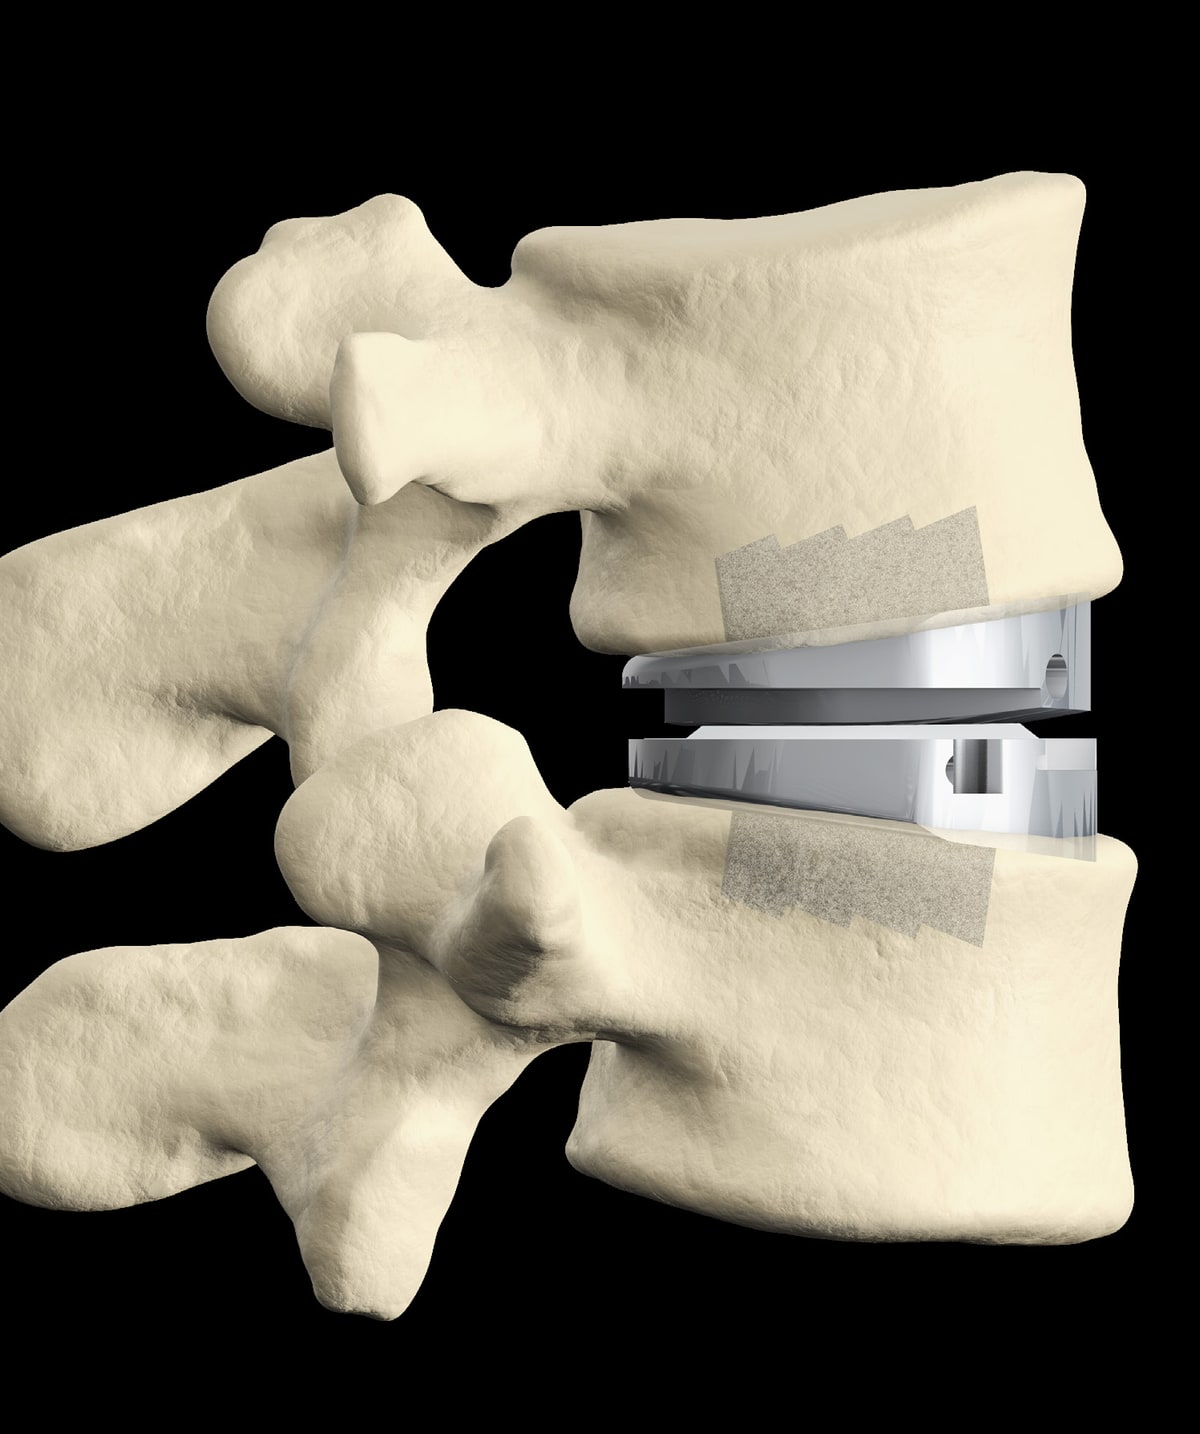
Side view of an artificial disc in the low back. Designs and sizes vary by patient and implant.


Images courtesy of Centinel Spine. Used with permission.
How care usually moves
Care usually starts without surgery. If surgery is reasonable, disc replacement is one path. Fusion or another approach may be a better fit for some problems.
-
Non-surgical care
Activity changes, medicine, physical therapy, and injections are common early options. Device labeling for lumbar artificial discs often describes failed nonsurgical care before implant surgery, unless a progressive problem changes the timing.
-
Disc replacement
Under general anesthesia, the approach is through a small incision in the abdomen. I typically work with a vascular access surgeon who helps carefully move the vessels and expose the front of the spine. The symptomatic disc is removed, the vertebrae are prepared, and the artificial disc—often metal endplates with a mobile core—is seated so the bones stay at a more normal height and can bend and twist at that level when the anatomy fits. Imaging guidance helps confirm position. The incision is then closed.
-
Other surgery
Anterior lumbar fusion remains a common alternative when motion preservation is not the right fit. Some low-back problems are better treated from the back of the spine. The choice is based on anatomy and goals.
Main risks
Risks depend on the path we choose.
- Infection, bleeding, or hematoma
- Injury to nearby vessels, organs, or the ureter
- Nerve injury, weakness, or changes in sensation
- Bowel or bladder changes; in men, possible sexual-function changes (including retrograde ejaculation)
- Ileus (slow return of bowel function) or hernia at the incision
- Implant loosening, migration, wear, subsidence, or unintended fusion at the level
- Symptoms that do not improve, or that return
- Need for more surgery later
- Allergy to implant materials
- Blood clots and other anesthesia-related risks
Device patient guides list additional rare but serious risks, including bleeding near major vessels. This list is not complete. We go over the main risks that apply to you before any procedure.
Recovery, in general
After surgery, some people go home sooner and others stay longer. Length of stay depends on pain control, how you are moving, and how your bowels and wound are doing.
Early recovery is usually about protecting the wound, walking as you are able, and building activity gradually as you are cleared. An abdominal brace may be used for support early on. Heavy lifting, prolonged strain, and extreme bending wait until it is safe. Physical therapy may be added later if it will help your progress.
Return to driving and desk work is discussed when you are comfortable, moving safely, and not needing strong pain medicine that would make driving unsafe. Timing varies. More physical work usually takes longer. We set those limits with you based on your job, your healing, and your exam.
While many people notice their preoperative back or leg symptoms ease soon after surgery, others still have symptoms that settle over weeks to months. Some new aches and soreness during healing are also common as your body adjusts. Recovery is not the same for everyone, and the goal is improvement—not a promise that every symptom will disappear. Call right away for fever, wound drainage, trouble swallowing or breathing, trouble urinating, or new or worse back or leg pain, numbness, or weakness.
Every patient is different; your plan may differ.
Related topics
Who this page is for
People considered for lumbar disc replacement often have low back pain from a worn disc that has been hard to live with for several months. In FDA-cleared labeling for these devices, candidates are usually adults whose bones are done growing, with pain tied to one or two neighboring discs in the lower lumbar spine, confirmed by history and imaging, and with little or no slip of the bones on each other. Nonsurgical care is usually tried first.
Common reasons this option may not fit include active infection, weak bone, a larger slip of the vertebra, allergy to implant materials, or other spine problems that need a different approach. Your visit and imaging decide the plan.
This page is general education. It is not a diagnosis and it is not a recommendation for a specific implant brand.
Seek emergency care for these signs
- Sudden loss of bowel or bladder control
- New numbness in the groin
- New, severe weakness in the legs
Call 911 or go to an emergency department. Tell your clinician about fever with new spine pain, a recent major infection, or a history of cancer with new spine symptoms.
Sources
Selected references used for this page:
- AAOS OrthoInfo — Lumbar Artificial Disk Replacement (leaves this website)
- Centinel Spine — prodisc L Patient Information Guide (PDF); figures used with permission (leaves this website)
- FDA Summary of Safety and Effectiveness — prodisc L Total Disc Replacement (PMA P050010/S020) (leaves this website)
- ISASS 2021 position statement on cervical and lumbar disc replacement (PMC) (leaves this website)
Request an appointment
To request an appointment, use my page on the Plano Orthopedic website.
Request an appointment (opens my page on the Plano Orthopedic website)